
Written by Matthew Travers, Co-Founder and President, Lead to Recovery. Updated October 17, 2026.
Starting a rehab center takes 14 steps in four phases: plan the program and its economics, fund and license it, contract with payers and market it, then open. The economics decide the rest. A residential program paid only by Medicaid breaks even near 95% occupancy, because state rates are built on that assumption. When one patient day in four is paid by a commercial plan, break-even occupancy falls to 59%, based on a South Dakota Medicaid rate model and national commercial claims data.
Key takeaways
Free worksheet: the 14-step pre-opening checklist, a line-item budget with published figures, and the break-even calculator from Step 3, in one printable PDF.
- Step 1: Choose Your Level of Care and Location
- Step 2: Run a Feasibility Study
- Step 3: Build Your Revenue Model and Break-Even Point
- Step 4: Price Your Startup Budget Line by Line
- Step 5: Secure Funding
- Step 6: Get Your Licenses and Permits
- Step 7: Write Your Policies and Procedures Manual
- Step 8: Hire Clinical Leadership and Staff
- Step 9: Design the Facility
- Step 10: Pursue Accreditation
- Step 11: Contract With Payers and Enroll in Medicaid
- Step 12: Build Your Marketing Before You Open
- Step 13: Build Programming on Evidence-Based Practices
- Step 14: Launch and Manage the First 90 Days
- How to Start a Rehab Center: FAQs
- Sources
Phase 1: Plan the program and the math
Step 1: Choose Your Level of Care and Location
In short: Decide what you will treat, for whom and at what ASAM level before you look at property, because zoning, licensing, staffing and revenue all follow from that choice.
A detox program needs 24-hour nursing and physician oversight. A residential program needs beds, a kitchen and overnight staff. An intensive outpatient program needs group rooms and evening hours. Outpatient is the most crowded market: 8.4 of every 10 substance use treatment facilities offer outpatient care, per SAMHSA’s 2024 N-SUMHSS.
Check five things before you sign anything:

Step 2: Run a Feasibility Study
In short: A feasibility study tests demand, money, regulation, staffing, the building and community support before you spend capital.
Cover six areas:
The output is a set of numbers you reuse in every later step: expected census, payer mix, staffing plan and licensing path. Those numbers become the core of your rehab center business plan.
Step 3: Build Your Revenue Model and Break-Even Point
In short: Price the program from what payers pay. Payer mix decides how full you need to be to cover costs.
Medicaid publishes what it pays. Montana Medicaid pays $264.66 a day for high-intensity residential care (ASAM 3.5) and $307.75 a day for medically monitored detox (ASAM 3.7) under its July 2025 fee schedule. Vermont pays $5,185 to $7,030 per high-intensity residential episode. Large employer health plans paid an average of $21,900 per residential treatment facility stay in 2023, and stays that included residential treatment averaged 19 days, per Peterson-KFF. The full table by level of care is in our study of what rehab costs in 2026.
What it costs to run a bed
South Dakota’s 2024 Medicaid rate study, prepared by Guidehouse, builds each residential rate from staff wages, a 35% benefits load, 39.2% administrative and program support, and a 95% occupancy assumption (South Dakota rate study). Its intensive inpatient rate plus room and board comes to $336.98 a day. At 95% occupancy, that equals $320.13 per available bed per day, or $2.34 million a year for a 20-bed program.
Treat that figure as a lean floor. Programs with more clinical hours, private rooms or amenities cost more to run.
Break-even occupancy by payer mix
| Payer mix (share of patient days) | Average revenue per occupied bed-day | Break-even occupancy |
|---|---|---|
| 100% Medicaid | $336.98 | 95.0% |
| 75% Medicaid, 25% commercial | $540.89 | 59.2% |
| 50% Medicaid, 50% commercial | $744.81 | 43.0% |
| 25% Medicaid, 75% commercial | $948.72 | 33.7% |
| 100% commercial | $1,152.63 | 27.8% |
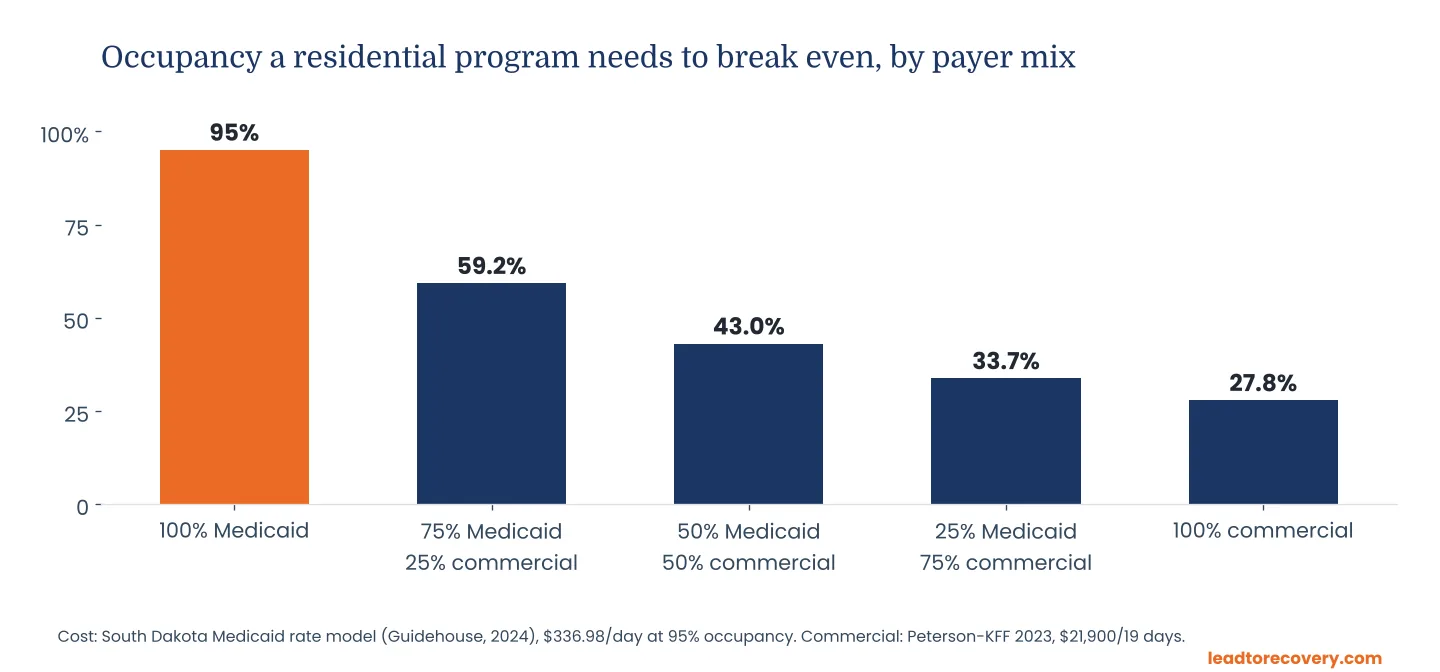
Figure 1. Break-even occupancy for a residential program by payer mix. Lead to Recovery analysis of the South Dakota Medicaid rate model and Peterson-KFF 2023 commercial claims data.
How we calculated it. Break-even occupancy equals the cost per available bed-day divided by the average revenue per occupied bed-day. The cost is $320.13 (the South Dakota model rate of $336.98 times 95%). Medicaid revenue is the same $336.98, so a Medicaid-only program breaks even at exactly the occupancy the state assumed. Commercial revenue is $21,900 divided by 19 days, or $1,152.63, an implied daily figure that includes professional fees and patient cost sharing.
Two cautions keep the model honest. Commercial plans authorize days through utilization review, so collected days run below admitted days. Programs built for commercial patients also staff above the Medicaid model, which raises the cost line. Replace each input with your state rate, contracted rates and staffing plan; the worksheet in the download does the math.
The conclusion holds at any reasonable input: a Medicaid-only residential program has almost no room for empty beds, and a modest share of commercial or private-pay patient days changes the business.
Step 4: Price Your Startup Budget Line by Line
In short: No public source publishes a reliable total startup cost for a rehab center, so build yours from line items with published prices and get written quotes for the rest.
The totals quoted around the web, such as “$500,000 to $2 million,” have no source behind them. These line items do:
| Line item | Published figure | Source |
|---|---|---|
| The Joint Commission behavioral health onsite survey | From $3,330 for a small organization, paid at the end of the survey | The Joint Commission |
| The Joint Commission annual fee | From $1,930 a year | The Joint Commission |
| CARF accreditation survey | Priced by the number of surveyors and survey days; request an estimate | CARF |
| DEA registration, opioid treatment program | $296 a year | 21 CFR 1301.13 |
| DEA registration, dispensing practitioner or clinic | $888 for three years | 21 CFR 1301.13 |
| Substance abuse and behavioral disorder counselor | $59,350 median annual pay (May 2025) | U.S. Bureau of Labor Statistics |
| Registered nurse | $97,550 median annual pay (May 2025) | U.S. Bureau of Labor Statistics |
| Operating cost, 20-bed residential program | About $194,700 a month ($320.13 per available bed-day) | South Dakota rate model, Lead to Recovery calculation |
| Treatment center website | $4,800 | Lead to Recovery pricing |
| Local SEO | $750 a month per location | Lead to Recovery pricing |
| Google Ads management | From $1,000 a month plus ad spend | Lead to Recovery pricing |
Get written quotes for the lease or purchase and build-out, general and professional liability insurance, the EHR system, state license and Certificate of Need fees, and furniture and equipment. Each one varies too much by state and building for a published figure to help.
Working capital is the line that sinks new programs
Staff must be on payroll before the state surveys you, and payers pay after the claim, so expenses start months before revenue. At the operating cost above, each month a 20-bed program runs before steady collections costs about $194,700. Multiply that by the months between your first hire and steady collections in your state, and fund the total before you sign the lease.
Phase 2: Fund, license and build
Step 5: Secure Funding
In short: Match each funding source to what it pays for, and show lenders the break-even table from Step 3.
Our guide to drug rehab center funding options covers each source in detail.
Step 6: Get Your Licenses and Permits
In short: State licensure is mandatory. Federal requirements apply once you handle controlled substances.
State behavioral health license
The state agency reviews your program description, staffing plan, policies and procedures manual, owner background checks and proof of financial solvency, then inspects the facility. Processing times vary by state, so ask the agency for its current timeline and plan your capital around it.
DEA registration
Required to dispense or administer controlled substances. The fee is $296 a year for an opioid treatment program and $888 for three years for a dispensing practitioner or clinic, under 21 CFR 1301.13.
Opioid treatment program certification
A program that dispenses methadone must hold a current certification under 42 CFR Part 8 and formally designate a medical director, who must be an actively licensed physician.
Certificate of Need
Some states require proof of unmet need before they approve a new healthcare facility. Confirm whether yours does before you commit capital.
Local permits
Building, occupancy, fire inspection and business licenses sit on top of the state license.
Step 7: Write Your Policies and Procedures Manual
In short: Surveyors and accreditors read the manual against what your staff actually do, so write it to match your real operations.
A complete manual covers:
Templates from behavioral health consultants speed up the first draft. Customize every policy to your program, because a gap between the manual and daily practice is a standard survey finding.
Step 8: Hire Clinical Leadership and Staff
In short: Licensing surveys check that key clinical roles are filled, so leadership hires come before the survey and before revenue.
This payroll runs before the first admission, which is why it sits inside the working capital line in Step 4.
Step 9: Design the Facility
In short: The building has to pass a state inspection for your level of care, then work for groups, privacy and supervision.
Step 10: Pursue Accreditation
In short: Licensure lets you operate. Accreditation opens payer contracts and tells families and referral sources that an outside body has reviewed your care.
CARF and The Joint Commission are the two main accreditors for addiction treatment. The Joint Commission accredits more than 3,500 organizations under its behavioral health manual, prices its onsite survey from $3,330 and its annual fee from $1,930. CARF prices each survey by the number of surveyors and survey days.
Accreditation is the norm among the programs families find first: in our audit of 100 top-ranking treatment center websites, 71 displayed Joint Commission or CARF accreditation.
See our guide to drug rehab center accreditation requirements.
Phase 3: Payers and patients
Step 11: Contract With Payers and Enroll in Medicaid
In short: Credentialing and Medicaid enrollment run on the payer’s clock, so start both as soon as your license allows.
Claims for patients treated before Medicaid enrollment is complete go unpaid unless your state allows provisional billing, so confirm the rule in your state.
Medicaid acceptance is a competitive opening. SAMHSA’s 2022 survey found that 74.2% of substance use treatment facilities accept Medicaid, yet in our website audit only 30 of 100 top-ranking centers said so on their site.
The Mental Health Parity and Addiction Equity Act requires most plans to cover substance use disorder treatment in a way similar to medical and surgical benefits. Document every denial. Our guide to drug rehab center insurance billing covers the revenue cycle.
Step 12: Build Your Marketing Before You Open
In short: Paid search produces calls once your certification clears, and organic search takes months, so both start before opening day.
What the first months look like
One of our clients, a new addiction and mental health treatment center in a low-population area, launched Google Ads on April 5, 2024 with no account history and no brand recognition. Cost per lead was $178.50 in the first month while the campaign collected data. By June it was $61.19. It held in the high $50s through the summer and reached $44.89 in October, 75% below launch (read the case study).
Budget the first three months at launch-month cost per lead, then expect it to fall as keywords, bids and ads are refined.
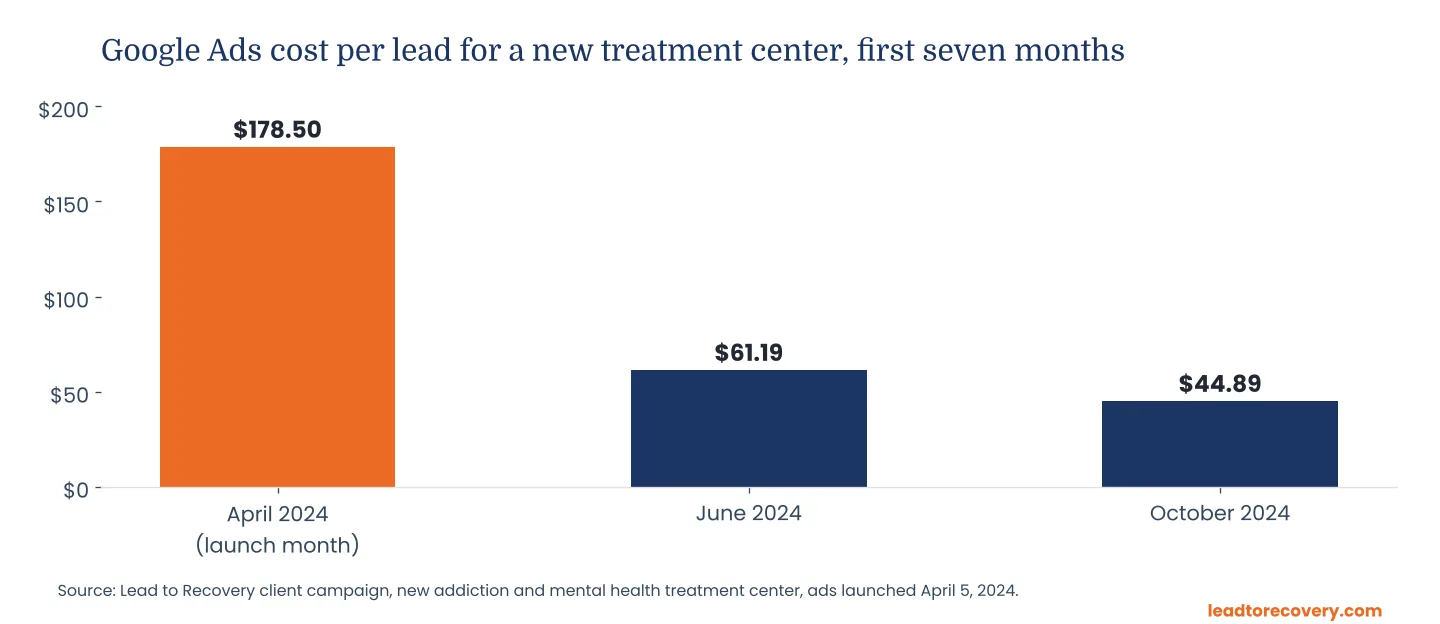
Figure 2. Google Ads cost per lead for a new treatment center in its first seven months. Lead to Recovery client data.
Certification comes before the first ad
Google restricts addiction treatment ads and requires certification before they run (Google Ads policy). Apply during licensing so the campaign is ready on opening day. Our LegitScript certification guide covers the process, and our Google Ads management for rehab centers starts at $1,000 a month plus ad spend.
Organic search
In a Pennsylvania engagement that began November 12, 2025, local SEO produced 108 first-time calls and 4 admissions at a $750 cost per admission in the first three months (case study). A New Jersey center on a $3,000-a-month regional plan reached 6 to 8 admissions a month from organic search within 180 days, at a $600 average cost per admission (case study). Both were operating centers. A new domain starts from zero, which is why the website and Google Business Profile go live before the license arrives. See drug rehab SEO.
A website built for admissions
Our treatment center website design starts at $4,800.
Step 13: Build Programming on Evidence-Based Practices
In short: Payers, accreditors and families look for treatment grounded in research, so name your methods in the program description and on your website.
Medication access is the widest gap. Of the 4.0 million Americans with an opioid use disorder in 2025, 15.7% received medication for it, per SAMHSA. A program that offers medications for opioid use disorder serves a population most competitors do not.
Phase 4: Open
Step 14: Launch and Manage the First 90 Days
In short: The first 90 days expose every gap in the plan, so track census, admissions and incidents weekly from the first day.
Questions operators ask
How to Start a Rehab Center: FAQs
Sources
- SAMHSA. “SAMHSA Releases Annual National Survey on Drug Use and Health (2025 NSDUH),” July 27, 2026.
- SAMHSA. “Companion Infographic Report: Findings from the 2024 National Substance Use and Mental Health Services Survey (N-SUMHSS),” 2025.
- SAMHSA. “N-SUMHSS 2022: United States Substance Use Treatment Profile,” reference date March 31, 2022.
- Guidehouse for the South Dakota Department of Social Services. “South Dakota Mental Health and Substance Use Disorder Rate Study,” January 5, 2024.
- Peterson-KFF Health System Tracker. “Cost and utilization of inpatient mental health and substance use treatment,” June 29, 2026.
- Montana Department of Public Health and Human Services. “SUD Medicaid Fee Schedule,” effective July 1, 2025.
- Vermont Department of Health. “DSU Medicaid Rate Sheet,” accessed October 2026.
- The Joint Commission. “Behavioral Health Care Accreditation Fact Sheet,” accessed October 2026.
- Code of Federal Regulations. “21 CFR 1301.13, Application for registration; time for application; expiration date; registration for independent activities,” current.
- Code of Federal Regulations. “42 CFR Part 8, Medications for the Treatment of Opioid Use Disorder,” current.
- U.S. Bureau of Labor Statistics. “Substance Abuse, Behavioral Disorder, and Mental Health Counselors, Occupational Outlook Handbook,” May 2025 pay data.
- U.S. Bureau of Labor Statistics. “Registered Nurses, Occupational Outlook Handbook,” May 2025 pay data.
- U.S. Small Business Administration. “7(a) loans,” accessed October 2026.
- U.S. Small Business Administration. “504 loans,” accessed October 2026.
- U.S. Department of Labor. “Mental Health and Substance Use Disorder Parity,” accessed October 2026.
- Google Ads Help. “Healthcare and medicines: addiction services policy,” accessed October 2026.
- Lead to Recovery. “How Much Does Rehab Cost in 2026? What 100 Treatment Center Websites Disclose,” October 17, 2026.
- Lead to Recovery client data: new treatment center Google Ads launch, Pennsylvania local SEO, New Jersey regional SEO.
This guide is general business information, not legal, tax, accounting or financial advice. Licensing, billing and financing rules vary by state; confirm decisions with qualified advisors and your state behavioral health agency.
Plan Your Launch Marketing Before Opening Day
Lead to Recovery builds the website, Google Business Profile, paid search and call tracking for new treatment centers before the license arrives, then reports every call and admission. Book a strategy call or call 855-876-7238.

